Pharmacological Toxicology: Metabolic Clearance, Blood-Brain Barrier & Host Vulnerabilities
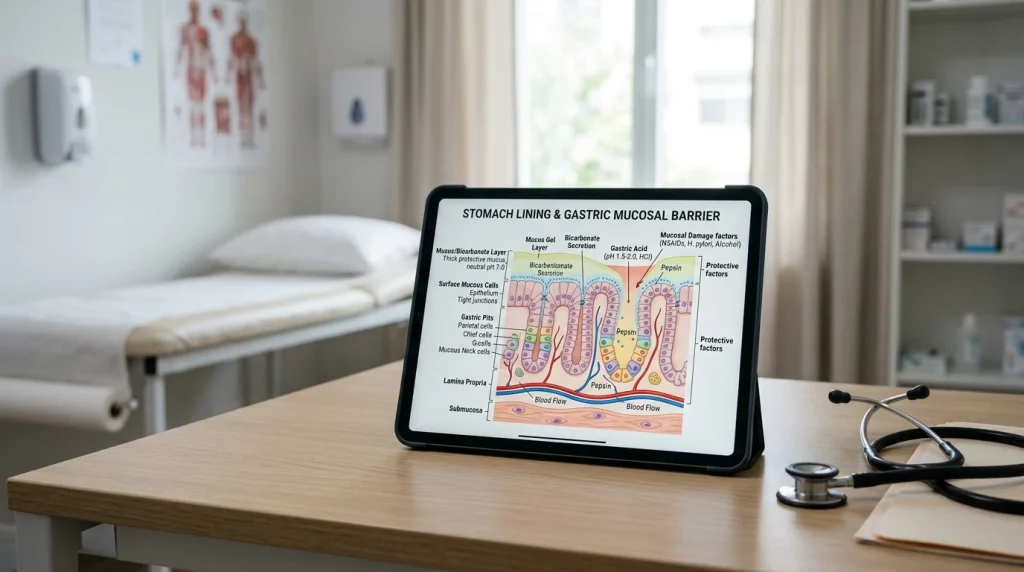
At therapeutic dosing thresholds in humans (150 to 200 mcg/kg), ivermectin possesses an exemplary safety profile because mammalian physiology lacks glutamate-gated chloride channels (GluCls). While mammalian central nervous system neurons express gamma-aminobutyric acid ($ ext{GABA}_A$) receptors—which share structural homology with GluCl channels—intact mammalian vascular endothelia maintain an active protective moat via the blood-brain barrier (BBB). Specifically, endothelial P-glycoprotein (an ATP-binding cassette transporter encoded by the ABCB1 gene) continuously extrudes ivermectin out of the cerebral capillary lumen back into the systemic circulation, preventing central nervous system penetration and neurotoxic depression.
However, when the therapeutic index is breached—either through deliberate massive overdose or genetic transporter impairment—severe neurotoxicity ensues. Symptoms follow a predictable continuum: initial lethargy, visual disturbances, and ataxia advance to tremors, stupor, respiratory depression, coma, and death. In veterinary medicine, dogs of herding lineage (including Collies, Shetland Sheepdogs, Australian Shepherds, and Old English Sheepdogs) frequently inherit an autosomal recessive 4-base-pair deletion mutation in the ABCB1 (MDR1) gene. Homozygous mutant dogs ($ ext{MDR1}^{-/-}$) lack functional P-glycoprotein efflux pumps, allowing standard antiparasitic doses to accumulate unimpeded across the blood-brain barrier, triggering catastrophic neurotoxicosis.
A critical toxicological distinction must also be maintained between intrinsic pharmacological side effects (mild transient nausea, headache, dizziness, abdominal discomfort) and immunologically mediated systemic responses. In filarial infections—specifically onchocerciasis—the sudden death of millions of microfilariae releases bacterial endosymbionts (such as Wolbachia) and antigenic structural proteins, triggering a severe systemic inflammatory cascade known as the Mazzotti reaction. Characterized by high fever, severe pruritus, urticaria, arthralgia, tender lymphadenopathy, tachycardia, and peripheral hypotension, the Mazzotti reaction represents host immune hyper-reactivity to dying parasites rather than direct chemical toxicity of the avermectin molecule.
| Patient / Target Group | Primary Toxicological Risk | Underlying Physiological Mechanism | Clinical Safeguard & Protocol |
|---|
| Pregnant Humans (1st Trimester) | Teratogenic risk / Fetal safety | Animal rodent models show cleft palate at maternotoxic doses. | Contraindicated; defer elective therapy until post-partum. |
| MDR1 Mutant Canine Breeds | Central Neurotoxicity / Coma | ABCB1 gene deletion; absent P-gp blood-brain barrier efflux. | Perform genetic PCR screen; restrict to heartworm prophylactic doses (6 mcg/kg). |
| High Microfilarial Loa loa | Fatal Encephalopathy | Massive microfilariae lysis occludes cerebral microvasculature. | Mandatory blood smear quantification prior to treatment. |
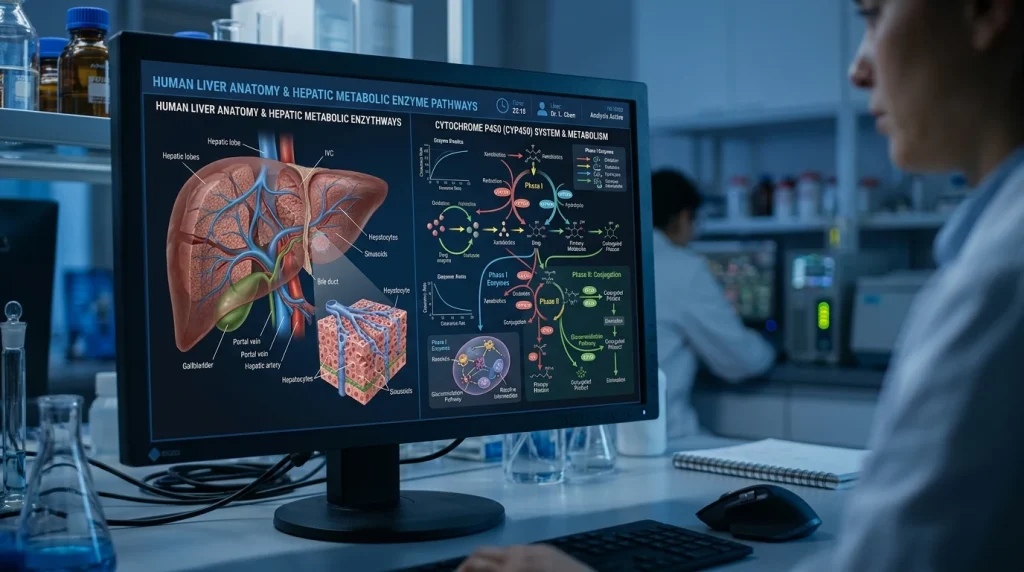
| Hepatic Impairment Patients | Elevated Serum Transaminases | CYP3A4 hepatic clearance overload; impaired biliary excretion. | Monitor ALT/AST levels; avoid concurrent potent CYP3A4 inhibitors. |
| Livestock Paste Ingestion | Acute Poisoning / Overdose | Massive avermectin concentration saturates blood-brain barrier. | Emergency toxicology hospital admission; supportive ICU airway care. |
Clinical Toxicology Notice: This educational category hub compiles published biomedical literature, pharmacovigilance reports, and veterinary toxicology registries for informational and scientific research purposes only. It does not provide certified medical emergency or toxicology counsel. In the event of suspected human or pet avermectin poisoning, immediately contact regional poison control or emergency veterinary medicine. Compiled by the Clinical Toxicology & Pharmacovigilance Reference Desk.